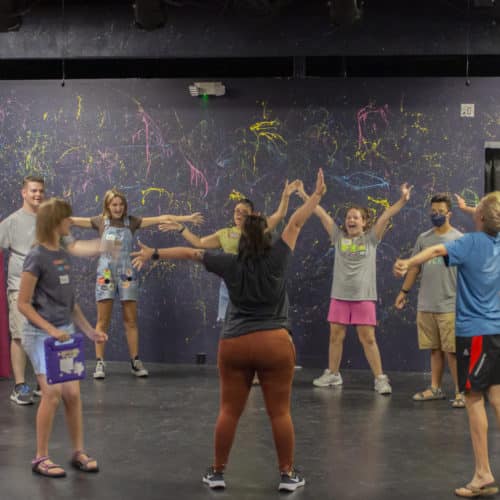Community Circles: Mental Health and Emotional Wellbeing


Community Circles events provide an opportunity to connect with other families and learn about community resources. Hosted by Children’s Clinics and Care 4 the Caregivers.

Care 4 the Caregivers Logo

This event is part of a series focused on creating connections for children and families with disabilities and complex medical needs.


2027 topics planned:

  • Deaf, Heard of Hearing, Blind, Low Vision, DeafBlind
  • Neurodevelopmental Disabilities
  • Medically Complex and Medically Fragile
  • Rare Diseases and Chromosomal Conditions


Registration: Community Circles - Mental Health and Emotional Wellbeing

"*" indicates required fields

Name*
Address*
Preferred Language*

Car Seat Safety Check

Did you know that about 70-80% of all car seats are installed incorrectly, putting your child at risk of injury? Come to Children’s Clinics to get your car seat professionally checked by a nationally certified Child Passenger Safety Technician – for FREE! *This event is for Children’s Clinics families only.

You must register to attend this event. This event is FREE. Car seat safety check appointments are in 30-minute time slots. You may register up to two children for a 30 minute time slot.

When: Wednesday, November 11th, 2026, 8:30am – 11:30am*
*You must register for a 30-minute appointment time slot

Where: Children’s Clinics parking lot, south side of the building

Cost: FREE

THINGS TO BRING:

  • your personal vehicle
  • current car seat
  • the child who uses that car seat

***Please note, this is not a car seat giveaway***

—

Evento de Revisión de Seguridad de Sillas de Auto Para Bebés

¿Sabía que entre el 70% y el 80% de las sillas de seguridad para niños se instalan incorrectamente, poniendo en riesgo a su hijo?
Venga a Children’s Clinics y haga que un técnico certificado a nivel nacional en seguridad de pasajeros infantiles revise su silla de seguridad de manera profesional, ¡totalmente gratis! Este evento es solo para familias de Children’s Clinics.

Las citas para la revisión de seguridad de sillas de auto se organizan en turnos de 30 minutos. Puede inscribir hasta a dos niños en un mismo turno de 30 minutos.

Cuándo: Miércoles, 11 de noviembre, 2026 de 8:30 AM – 11:30 AM.*
*Debe inscribirse para un intervalo horario de cita de 30 minutos.

Dónde: Estacionamiento de Children’s Clinics; lado sur del edificio

Costo: Gratuito

Cosas que debe traer:

    • su vehículo
    • al bebé
    • la silla de auto actual

***Por favor, tenga en cuenta que esto no es un sorteo de sillas de auto***

Cleft Family Picnic

We are excited to celebrate our children born with cleft lip, palate, and other craniofacial differences at our first picnic! Where kids can do what they do best: have fun. Where parents can connect with others on a similar journey. Where new friendships begin!

Ramada 1 is ADA Accessible, has electrical outlets, 2 picnic tables, lights, BBQ grills, a drinking fountain, attached bathrooms, and is right next to the playground.  

As there are only two picnic tables available, families should plan to bring chairs/picnic blankets. 

Light snacks will be provided.

Register by Friday, October 9th

Registration: Cleft Family Event

"*" indicates required fields

Name*
Address*

Informed Consent to Photograph or Record | Cleft Family Event

Patients attending the event are invited to participate in a short video that will be used to help prepare future patients for their scoping procedures. Patients with a signed photo/video release are welcome to take part.
I consent on behalf of the above-named patient to video recording by Children's Clinic staff.
I agree the resulting images or recordings may be used for Children’s Clinics publicity or marketing (brochure, pamphlet, bulletin board, display, informational video, magazine article)
I prefer to opt out of participating in this video on behalf of the above-named patient.
I understand I have the right to reverse this consent, in writing , at any time before the image or recording is used for the purpose(s) indicated above.
Signature of Parent/Guardian or Legally Authorized Representative completing this form (or patient, if over 18)
Date
Signature of Witness
Date


Adaptive Tennis 2026

**Tennis Registration is now full. Please register below if you would like to be added to the waitlist.

Join our 7-week session of Adaptive Tennis sponsored by Elizabeth Read Taylor Foundation! Participants will learn the fundamentals of tennis with a supportive and inclusive community. All abilities are welcome!!!

Location: Tucson Racquet Club I 4001 N Country Club Rd, Tucson, AZ 85716

Dates: Tuesdays October 6- November 10 2026

Times: Group 1 – 5:30pm – 6:30pm and Group 2 – 6:30pm – 7:30pm (Groups are based on both age AND ability)

**Tennis Registration is now full. Please register below if you would like to be added to the waitlist. 

Adaptive Tennis Registration 2026

    Please check all that apply.
  • (English, Español, etc)
  • (English, Español, etc)
  • Please identify an individual other than yourself that we can contact in case of an emergency. / Por favor identifique a un individuo aparte de usted mismo que podamos contactar en caso de emergencia
  • Example (Please list all that apply): - Speech / Hablado - Other Sounds / Otros Sonidos - Eye Gaze / Mirada - Gestures / Gestos - A communication device / Un aparato de comunicación
  • Example (Please list all that apply): - Short Simple Directions / Instrucciones cortas y simples - Repetition / Repetición - Face to face communication / Comunicación cara a cara - Speaking at a slow pace / Hablar lento
  • Example (Please list all that apply): - crawling / gateando - walking with assistance / camina con asistencia - walking with out assistance / camina sin asistencia - wheeled mobility / movilidad con ruedas - other assistive device / otro aparato de asistencia
    I understand that I must remain and be present at the venue for the duration of the program while my child participates in dance. / Entiendo que debo permanecer presente durante la duración del programa mientras mi hijo participa en futbol
    I authorize my child to participate in Children’s Clinics Childhood Experiences Programs. I acknowledge the risks inherent in the participation by my child. In my absence, I further authorize the staff representing Children’s Clinics to act for me according to their best judgment in any emergency requiring medical attention for my child and I hereby waive and release those staffers, and volunteers of Children’s Clinics from all liability for any injuries or illnesses, that may be incurred while participating in Children’s Clinics Childhood Experiences, while in attendance, except for injury directly resulting from gross negligence or willful misconduct. /Autorizo que mi hijo participe en los Programas de Experiencias Infantiles de la Clínica de los Niños. Reconozco los riesgos adjuntos a la participación de mi hijo. En mi ausencia, autorizo al personal representante de la Clínica de los Niños a actuar por mi acorde a su mejor juicio en cualquier emergencia que requiera atención médica para mi hijo y por el presente exento y libero a esos empleados y voluntarios de la Clínica de los Niños de toda responsabilidad de cualquier lesiones o enfermedades que pudieran adquirir mientras participan en Experiencias Infantiles de la Clínica de los Niños, mientras atienda, excepto por lesiones resultantes directamente de negligencia grave o mala conducta intencional.
    I consent to the photographing/video recording/ audio recording of the above-named patients by Children's Clinics staff at this event. I agree the resulting images or recordings may be used for Children's Clinics publicity or marketing purposes (brochure, pamphlet, lobby display, social media posts, printed material, etc.). I understand that I have the right to reverse this consent, in writing, at any time before the image or recording is used for the purposes indicated above. / Yo consiento la toma de fotografías/grabación de video/grabación de audio de los participantes mencionado anteriormente por el personal de la Clínica de los Niños en este evento. Estoy de acuerdo con que las imagines o grabaciones resultantes sean usadas para los propósitos de publicidad o marketing (folleto, panfleto, exposición en el vestíbulo, publicaciones de redes sociales, materiales impresos, etc.). Entiendo que tengo el derecho de revertir este consentimiento, en escrito, en cualquier antes de que la imagen o grabación sean usados para los propósitos indicados anteriormente.
    I understand that the information provided in this registration form may be accessed and reviewed by staff, therapists, instructors, and volunteers involved in this adaptive rec program to ensure the best possible support for the participant. / Entiendo que la información proporcionada en este formulario de inscripción puede ser accedida y revisada por el personal, terapeutas, instructores y voluntarios involucrados en este programa de recreación adaptada para garantizar el mejor apoyo posible al participante.

Adaptive Theatre and Improvisation

This five-week program engages the Children’s Clinics community in various theatre games. 

The goal is to support participants in exploring their imagination, creativity, and improvisation skills to build confidence and community – all in the spirit of joy and fun!

Adaptive Theatre and Improvisation Registration 2026

    Our team will contact you if a spot opens up in our program. / Nuestro equipo se pondrá en contacto con usted si queda un cupo disponible en nuestro programa.
    Participants who have not been able to participate with Saguaro City programs in 2006 will be given priority for our Adaptive Theatre and Improvisation class at Children’s Clinics. / Se dará prioridad para nuestra clase de Teatro Adaptativo e Improvisación en Children’s Clinics a los participantes que no hayan podido participar en los programas de Saguaro City en 2006. 
    Please check all that apply.
  • (English, Español, etc)
  • (English, Español, etc)
  • Please identify an individual other than yourself that we can contact in case of an emergency. / Por favor identifique a un individuo aparte de usted mismo que podamos contactar en caso de emergencia
  • Example (Please list all that apply): – Speech / Hablado – Other Sounds / Otros Sonidos – Eye Gaze / Mirada – Gestures / Gestos – A communication device / Un aparato de comunicación
  • Example (Please list all that apply): – Short Simple Directions / Instrucciones cortas y simples – Repetition / Repetición – Face to face communication / Comunicación cara a cara – Speaking at a slow pace / Hablar lento
  • Example (Please list all that apply): – crawling / gateando – walking with assistance / camina con asistencia – walking with out assistance / camina sin asistencia – wheeled mobility / movilidad con ruedas – other assistive device / otro aparato de asistencia
    I understand that I must remain and be present at the venue for the duration of the program while my child participates in dance. / Entiendo que debo permanecer presente durante la duración del programa mientras mi hijo participa en futbol
    I authorize my child to participate in Children’s Clinics Childhood Experiences Programs. I acknowledge the risks inherent in the participation by my child. In my absence, I further authorize the staff representing Children’s Clinics to act for me according to their best judgment in any emergency requiring medical attention for my child and I hereby waive and release those staffers, and volunteers of Children’s Clinics from all liability for any injuries or illnesses, that may be incurred while participating in Children’s Clinics Childhood Experiences, while in attendance, except for injury directly resulting from gross negligence or willful misconduct. /Autorizo que mi hijo participe en los Programas de Experiencias Infantiles de la Clínica de los Niños. Reconozco los riesgos adjuntos a la participación de mi hijo. En mi ausencia, autorizo al personal representante de la Clínica de los Niños a actuar por mi acorde a su mejor juicio en cualquier emergencia que requiera atención médica para mi hijo y por el presente exento y libero a esos empleados y voluntarios de la Clínica de los Niños de toda responsabilidad de cualquier lesiones o enfermedades que pudieran adquirir mientras participan en Experiencias Infantiles de la Clínica de los Niños, mientras atienda, excepto por lesiones resultantes directamente de negligencia grave o mala conducta intencional.
    I consent to the photographing/video recording/ audio recording of the above-named patients by Children’s Clinics staff at this event. I agree the resulting images or recordings may be used for Children’s Clinics publicity or marketing purposes (brochure, pamphlet, lobby display, social media posts, printed material, etc.). I understand that I have the right to reverse this consent, in writing, at any time before the image or recording is used for the purposes indicated above. / Yo consiento la toma de fotografías/grabación de video/grabación de audio de los participantes mencionado anteriormente por el personal de la Clínica de los Niños en este evento. Estoy de acuerdo con que las imagines o grabaciones resultantes sean usadas para los propósitos de publicidad o marketing (folleto, panfleto, exposición en el vestíbulo, publicaciones de redes sociales, materiales impresos, etc.). Entiendo que tengo el derecho de revertir este consentimiento, en escrito, en cualquier antes de que la imagen o grabación sean usados para los propósitos indicados anteriormente.
    I understand that the information provided in this registration form may be accessed and reviewed by staff, therapists, instructors, and volunteers involved in this adaptive rec program to ensure the best possible support for the participant. / Entiendo que la información proporcionada en este formulario de inscripción puede ser accedida y revisada por el personal, terapeutas, instructores y voluntarios involucrados en este programa de recreación adaptada para garantizar el mejor apoyo posible al participante.

Saguaro City Music Theatre – Clean Slate

Saguaro City Music Theatre’s CLEAN SLATE is a high-energy, hands-on course designed to help young performers learn what musicals are all about and how to audition for them. By the end of this 5-week program, each student knows how to do a vocal warm-up, has one audition-ready song, receives sheet music for this song in the correct key, gets a rehearsal track to practice at home, and walks away with a professional headshot and resume that SCMT provides!

Registration will open for Saguaro City Music Theatre’s Clean Slate Audition Workshop on Wednesday, May 20th at 7AM.

This program is tuition-free and offered on a first-come, first-served basis. Spots are limited and will fill quickly. We encourage families to register as soon as possible!

DATES: Fridays, July 17th – August 14th

PROGRAM TIMES:

  • Ages 7-11: 5pm-7pm
  • Ages 12-17: 7:15pm-9:15pm

LOCATION: Kids Unlimited Studios | 6066 N. Oracle Rd.

REGISTRATION OPENS: Wednesday, May 20th, at 7am

REGISTER HERE: https://www.saguarocity.org

QUESTIONS?

  • Email: studio.arts@saguarocity.org
  • Phone: 520-809-5729

Adaptive Dance Hip-Hop 2026 in Partnership with Phoenix Suns/Phoenix Mercury Foundation

Adaptive Dance is back!

Turn up the music and let’s get moving! This 5-week adaptive hip hop class is all about having fun, trying new moves, and bringing your own style to the dance floor. Inspired by the fundamentals of Drop Studio instructors Ruben Dorame and Midnight Joe, dancers will learn cool hip hop basics, find the beat, and even try a little freestyle!

We’ll bounce, groove, and play with movement in ways that work for you, whether you’re dancing standing, seated, or mixing it up. Every class is all about creativity, confidence, and celebrating what your body can do.

No hip hop or dance experience needed. Just come ready to move and have a great time!

Location: The Drop Dance Studio | 716 E 46th St, Tucson, AZ 85713

Instructors: Ruben Dorame and Midnight Joe from the Drop Dance Studio

Dates: Thursdays, June 4th – July 2nd, 2026 (5 week program)

Times: 

Group 1 – 5:30 pm – 6:30 pm

Group 2 – 6:30 pm – 7:30 pm

(Groups are based on both age AND ability)

Recommended Age: 5yr – 22 yr

Our Adaptive Dance Program is now FULL. Please register below if you would like to be added to our waitlist.

Saguaro City Music Theatre – Summer Camp

STUDIO ARTS PRESENTS is a three-week musical theatre camp focused on learning, rehearsing, and performing a live, professional-quality musical theatre production for the public. Participants learn music, choreography, and staging alongside professional adult performers to create a one-of-a-kind production experience.

This program is tuition-free and offered on a first-come, first-served basis. Spots are limited and will fill quickly. We encourage families to register as soon as possible.

IMPORTANT DATES:

Camp at Pima Community College – West Campus

WHEN: Saturday, June 6 | 9 AM-3 PM

Monday-Friday, June 8-19 | 9 AM-3 PM

Camp at The Berger Performing Arts Center

WHEN: Monday-Friday, June 22-26 | 9 AM-3 PM

Performances at The Berger Performing Arts Center

WHEN: Friday, June 26th, 3 PM

Saturday, June 27th, 11 AM & 3 PM (Camper start time 10 AM)

Sunday, June 28th, 11 AM & 3 PM (Camper start time 10 AM)

***All registered campers will be cast in the summer production, but are required to attend a pre-camp audition. Audition information will be provided after your registration is complete. 

Registration opens Tuesday, March 17 at 7 AM via Studio Arts website. Register HERE!

If you have any questions, please reach out to studio.arts@saguarocity.org or (520) 809-5729.

Teen Sibshop (13-17)

Brothers and sisters, ages 13 to 17, with siblings who have complex medical needs, have feelings that may be hard to express, even to a friend. Sibshop is that safe space that allows them to explore and express their feelings and meet others with shared experiences who truly understand. Sibshop celebrates the many contributions made by brothers and sisters to the family and engages them through fun and interactive games.

Sibshop Is Just For Siblings To

  • Laugh
  • Have fun
  • Play games
  • Talk about the good and not-so-good parts of having a sibling with special needs
  • Spend time with other siblings who “get it”
  • A chance to be heard and seen

This group meets every second Thursday of the month until June 11, 2026. Then it will meet the first Thursday of every month starting on July 2, 2026. If you’re new to the group, please register for the event. (2026 Dates: 6/11, 7/2, 8/6, 9/3, 10/1, 11/5, 12/3)

Sibshop Registration

"*" indicates required fields

Participant's Name*
Participant's preferred language*
If other than English, does the participate speak English?
Is the participant a patient at Children's Clinics?*
What is the name of the sibling with a disability?*
(If more than one sibling with a disability list below)
Is the sibling with a disability a patient at the Children’s Clinics?*
For example, Megan Jones is 14 years old, born on 01/01/2010. She is a patient at the Children’s Clinics with cerebral palsy.
Does the Participant have siblings without a disability?*
For example: Megan Jones age 14, Jose Martinez age 12
Parent/Guardian Name*
Parent/Guardian's Preferred Language*
If other than English, does the parent/guardian speak English?
How do you prefer to be contacted?*
Address*
Please identify an individual other than yourself that we can contact in case of an emergency.
Please check that you have read and agree to the following:*
I consent to the photographing/video recording/ audio recording of the above-named patients by Children's Clinics staff at this event. I agree the resulting images or recordings may be used for Children's Clinics publicity or marketing purposes (brochure, pamphlet, lobby display, social media posts, printed material, etc.). I understand that I have the right to reverse this consent, in writing, at any time before the image or recording is used for the purposes indicated above.
Agreement: I agree to stay at Children's Clinics throughout the duration of the group for my child.*